INITIAL SPINE CONSULTATION
HISTORY OF PRESENT ILLNESS:
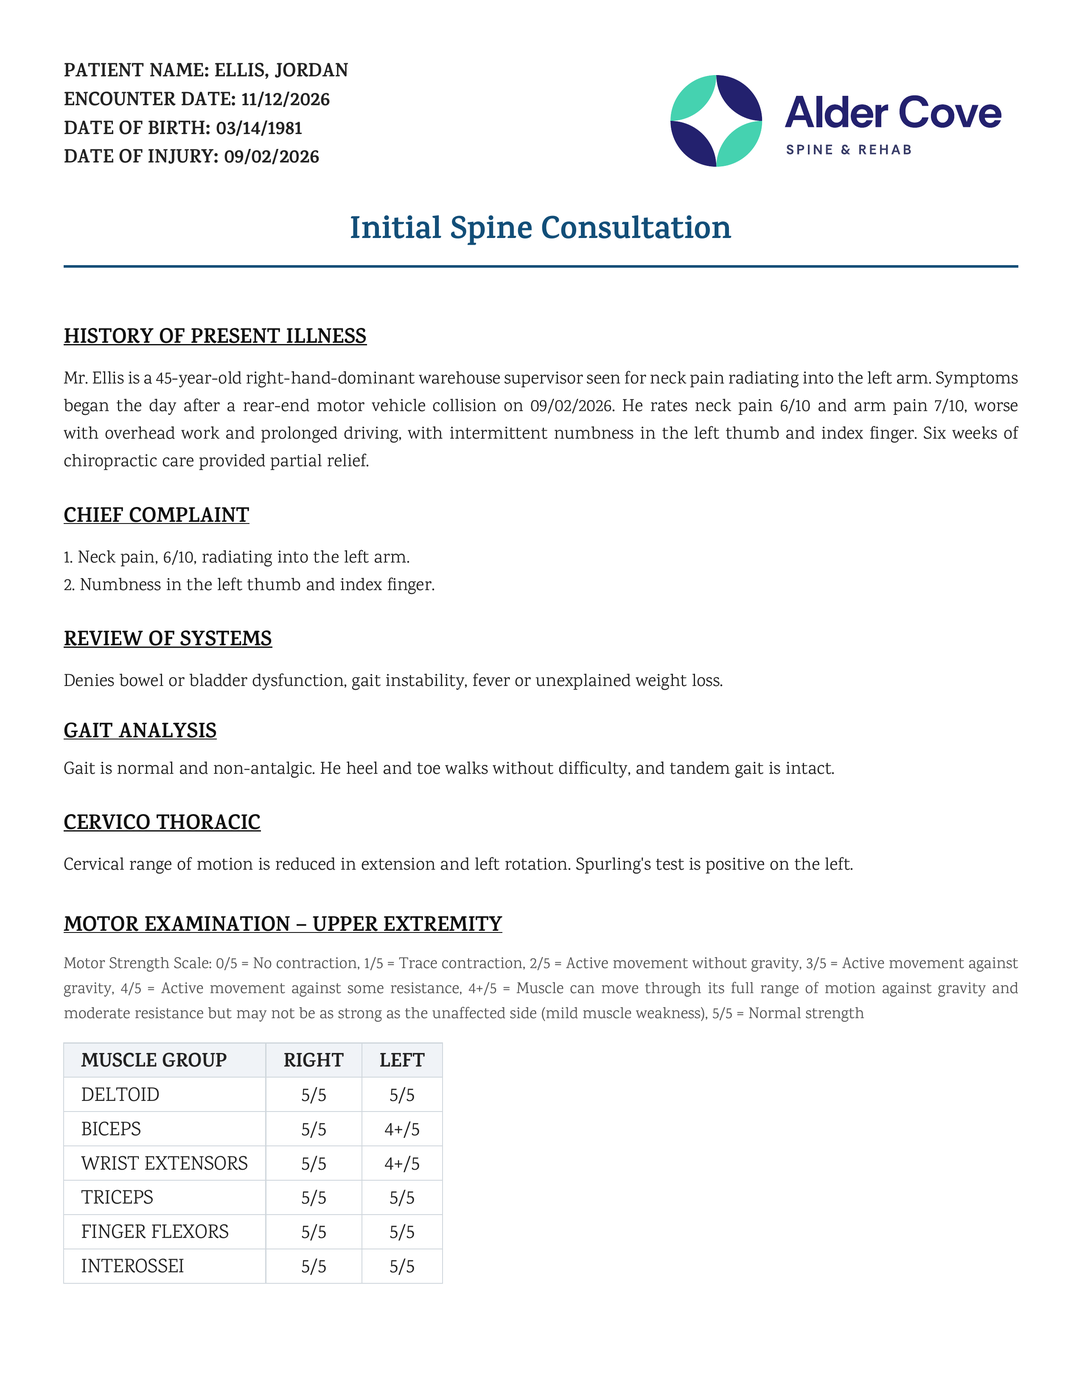
Mr. Ellis is a 45-year-old right-hand-dominant warehouse supervisor seen for neck pain radiating into the left arm. Symptoms began the day after a rear-end motor vehicle collision on 09/02/2026. He rates neck pain 6/10 and arm pain 7/10, worse with overhead work and driving, with intermittent numbness in the left thumb and index finger.
Your headings, in your orderCaps, underline and colon, as you set themPHYSICAL EXAMINATION:
Cervical range of motion is reduced in extension and left rotation. Spurling’s test is positive on the left. Strength is 5/5 throughout the upper extremities except the left biceps and wrist extensors, 4+/5. Left biceps and brachioradialis reflexes are 1+; right are 2+. Hoffmann’s sign is negative bilaterally. Pinprick is decreased in the left C6 dermatome.
Gait is normal and non-antalgic. He heel and toe walks without difficulty, and tandem gait is intact.
You said “normal gait”Your standard sentence, highlighted until you review itIMAGING:
MRI of the cervical spine dated 10/20/2026 shows a left paracentral disc protrusion at C5-6 with moderate left foraminal narrowing.
IMPRESSION:
- Left C6 radiculopathy.
- C5-6 left paracentral disc protrusion.
PLAN:
Left C5-6 interlaminar epidural steroid injection. Continue home exercise program. Return in six weeks.
CAUSATION:
Within a reasonable degree of medical probability, the patient’s cervical injuries are causally related to the motor vehicle collision of 09/02/2026.
Your causation wordingWord for word, every timeBoard Certified, Orthopaedic Surgery